
Health systems operate in an increasingly punishing economic landscape. As hospital median operating margins hover at a razor-thin 1.7 percent, clinical and financial leaders must scrutinize every operational process for efficiency and cost recovery. While traditional growth strategies heavily rely on high-cost physician recruitment or broad consumer marketing campaigns, an overlooked lever for organic growth lies in optimizing existing care networks. Health systems frequently fail to realize that patients are migrating to competitors or dropping out of their care pipeline entirely, resulting in what is collectively known as hidden referral leakage.
At the center of this challenge is a fundamental clinical transaction: the patient referral. Every year, U.S. healthcare systems lose an estimated $150 billion to referral leakage and incomplete care transitions. Understanding what referral pathways exist and how they operate is crucial, yet the administrative complexity of coordinating these transactions often transforms what should be a seamless handoff into a frustrating maze for patients and providers alike. For health systems, this fragmentation represents a silent and progressive drain on operating margins that traditional financial dashboards fail to capture.
What Is a Referral in Healthcare?
In the context of clinical operations, a referral is formally defined as a request from one clinician to another for the evaluation, treatment, or co-management of a patient's condition. Unlike a standard medical order (which represents a direct clinical instruction for a specific diagnostic test or intervention, such as a routine laboratory blood draw), a referral is a transition of clinical responsibility. It occurs when a patient's clinical complexity exceeds the scope of their primary care, requiring the referring physician to seek the diagnostic acumen of a referred doctor or specialist.
The process begins when an ordering provider generates a clinical referral, outlining the patient's active symptoms, diagnostic history, and the specific clinical question that requires expert collaboration. For example, a general practitioner evaluating a patient with persistent joint pain might prepare a formal referral letter to transition the patient's care to an orthopedic surgeon. Similarly, a general practitioner may write a GP letter for mental health services to connect a patient with a licensed psychiatrist or behavioral health therapist for specialized, ongoing care.
Regardless of the clinical scenario, the operational processes of a referral centers on structured collaboration. The goal is to ensure that relevant patient history and clinical context flow securely between providers, allowing the consulting physician to deliver appropriate, timely care. In a high-functioning health system, the primary care physician remains the central coordinator, reviewing specialist findings to integrate them back into the patient's permanent medical record.
The Core Types of Medical Referrals
The clinical and operational pathways of a referral vary depending on the patient's needs, the urgency of the condition, and the setting in which care is delivered. When analyzing these transitions, clinical teams typically classify them into three types of medical referrals:
1. Specialist Referrals
This is the traditional and most common clinical transition, where a primary care clinician refers a patient to a physician with advanced training in a specific sub-specialty. This category includes consultations for newly identified conditions requiring diagnostic evaluation, as well as ongoing follow-up referrals for chronic disease management.
2. Diagnostic Referrals
A diagnostic referral is a clinical directive for a patient to undergo specialized diagnostic testing, such as an MRI, CT scan, ultrasound, or complex laboratory assessment. Because these tests often carry high technical fees, retaining these referrals in-network is vital for maximizing service-line utilization and protecting health system margins.
3. Ambulatory Referrals
Health system leaders must understand the operational distinction of an ambulatory referral. An ambulatory referral is a clinical order for a patient to receive specialized evaluations, diagnostic tests, or therapy services on an outpatient basis. Because these services do not require an overnight hospital stay, they represent a high-volume, highly steerable care segment that heavily influences outpatient margins.
In addition to these core categories, clinical urgency dictates specific scheduling pathways. For acute, clinically unstable, or time-sensitive conditions, providers utilize a stat referral. A stat referral bypasses standard outpatient scheduling queues, triggering immediate clinical triage and rapid-response intake workflows to ensure the patient is evaluated without delay.
How the Healthcare Referral Process Actually Works
To the casual observer, the healthcare referral process seems straightforward: a doctor recommends a specialist, and the patient schedules an appointment. In practice, however, the workflow involves a complex lifecycle of five operational stages, each represents a potential failure point where patients can fall through the cracks.
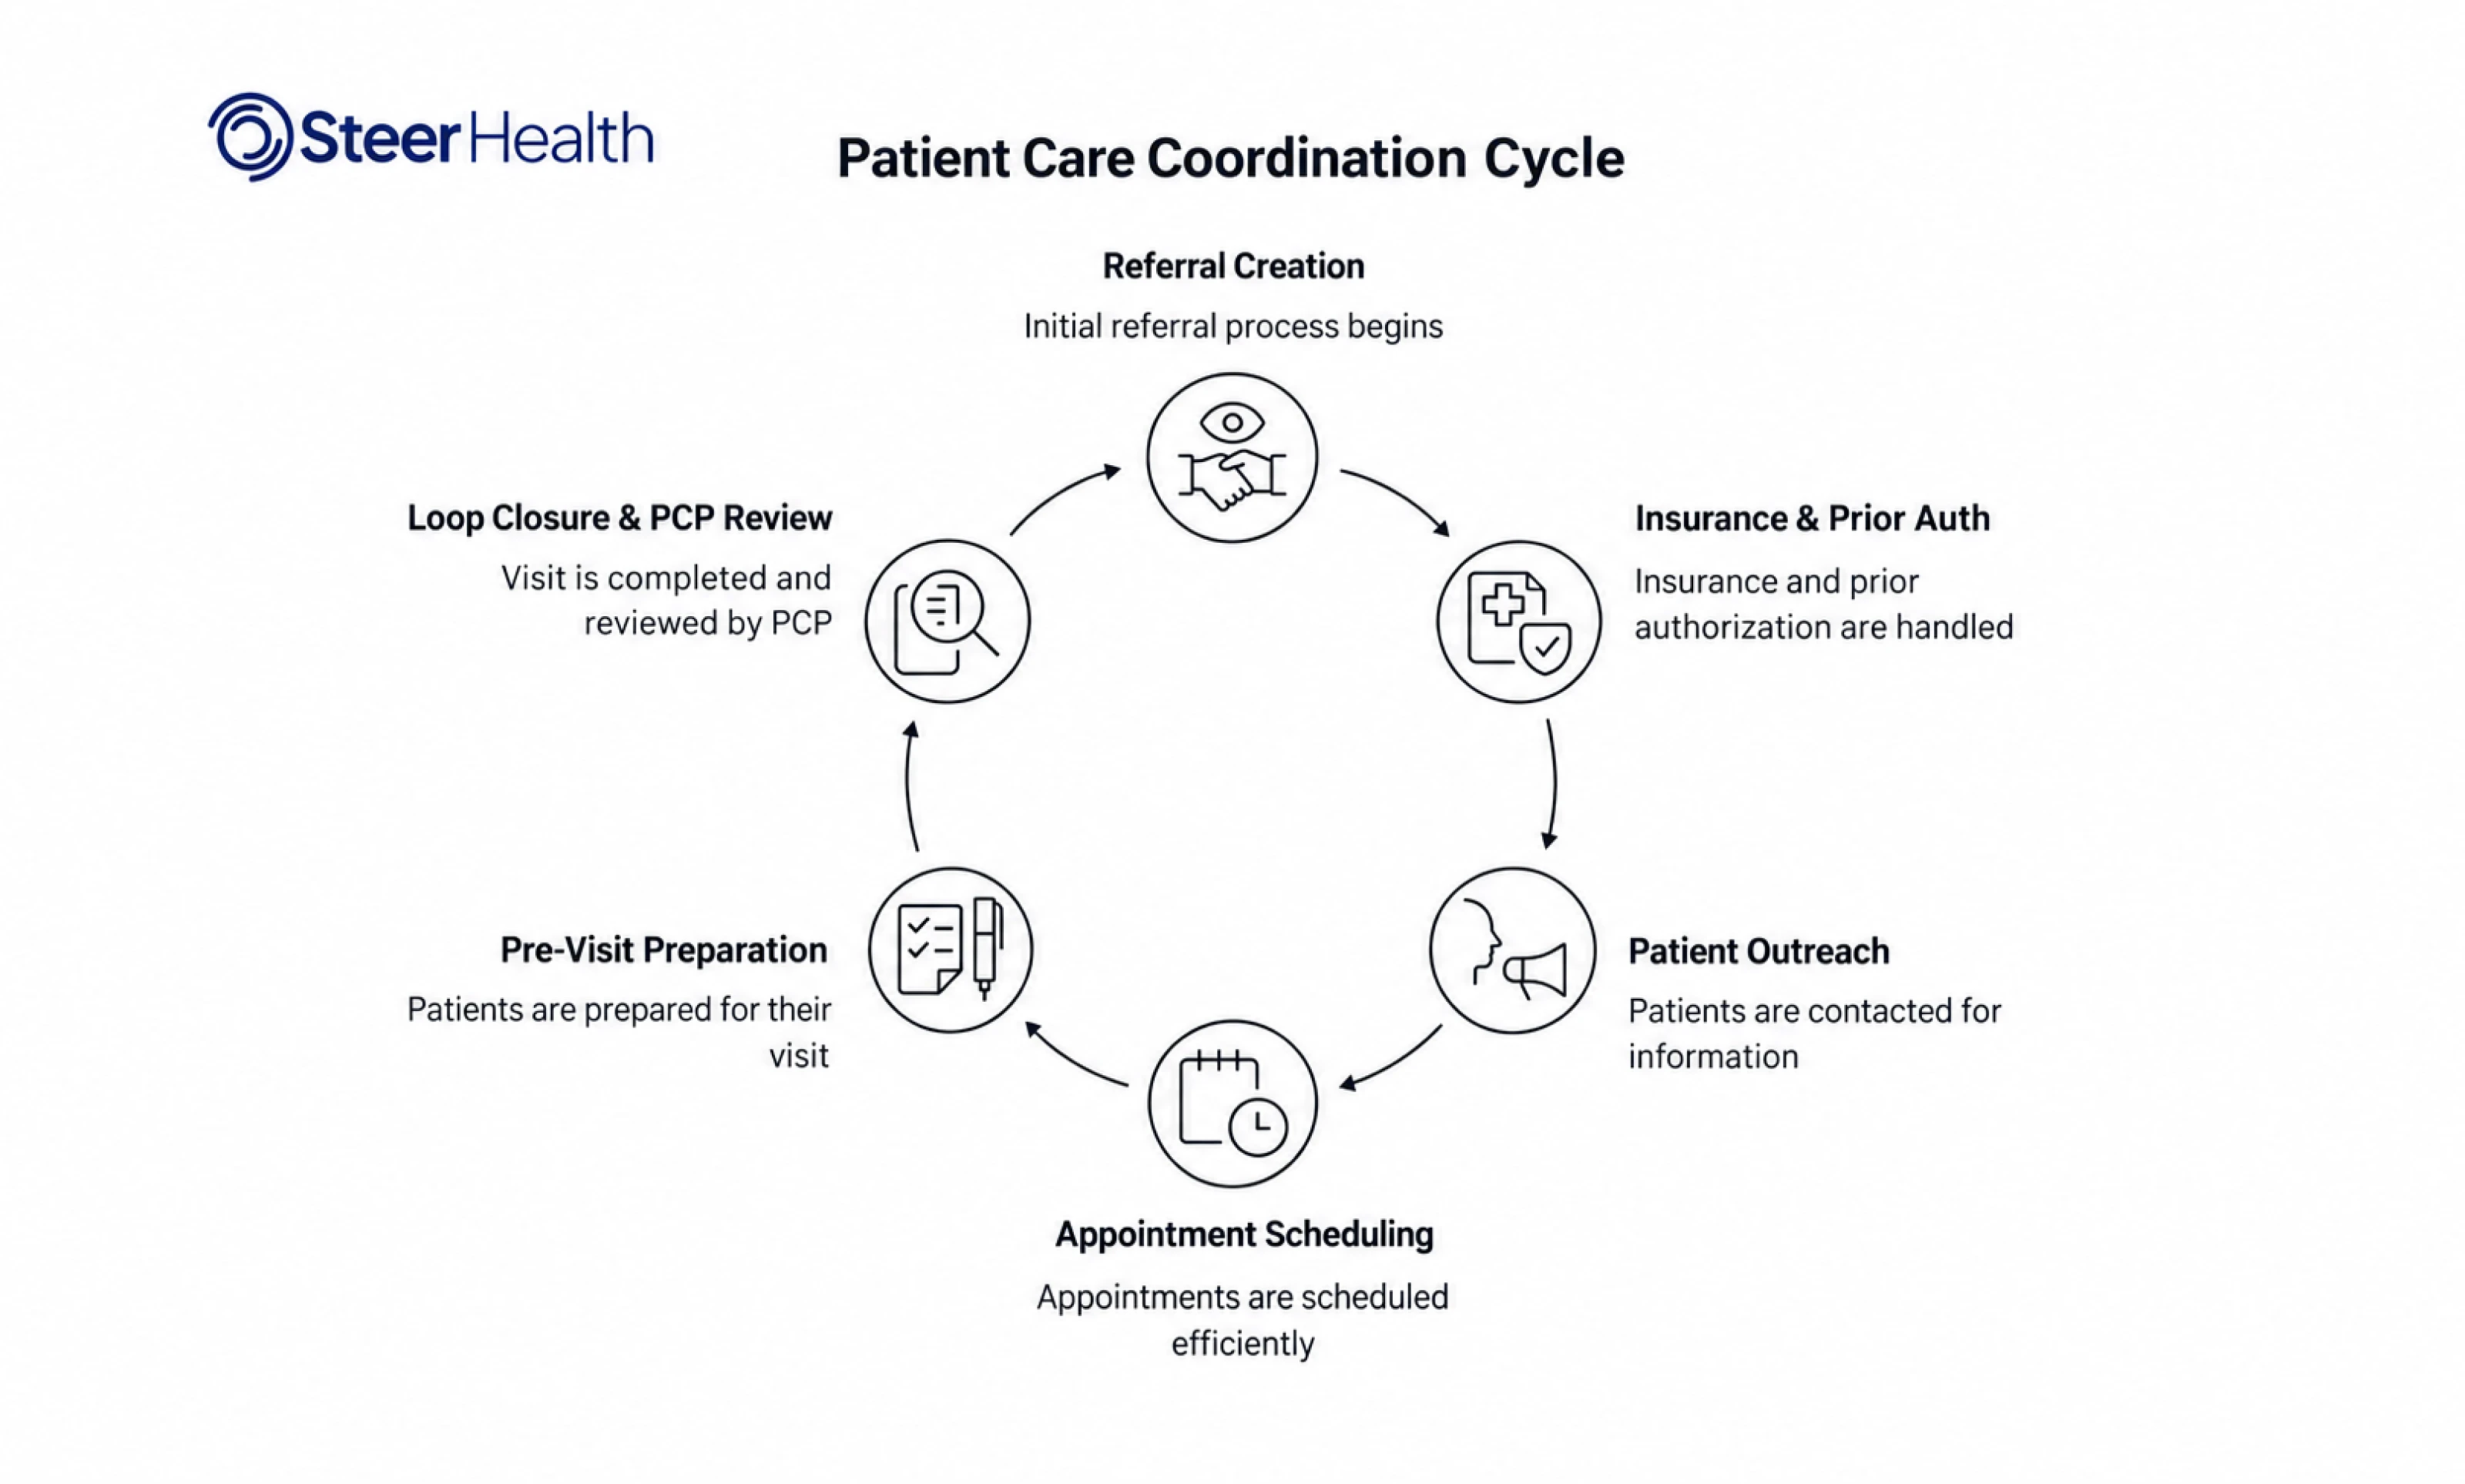
Stage 1: Referral Creation
The ordering clinician identifies a clinical need and enters a referral order within the electronic health record (EHR). For the referral to proceed efficiently, the initiating office must attach a complete referral letter detailing the clinical question, relevant medical history, and previous diagnostic workup. Incomplete documentation at this stage is a leading cause of coordinator backlog and scheduling delays.
Stage 2: Insurance Verification and Prior Authorization
Before scheduling can occur, the referral staff must verify the patient's insurance network status and secure formal prior authorization from the payer. This is an incredibly tedious, manual process that requires coordinators to log into various payer portals, upload clinical documentation, and monitor approval status, often stalling the transition of care for two to seven days.
Stage 3: Patient Outreach and Education
Once authorized, staff contact the patient to explain the referral and coordinate scheduling. This stage represents the highest failure rate in the entire lifecycle. Patients frequently do not answer calls from unknown numbers, leading to a prolonged cycle of phone tag that leaves many patients completely lost to follow-up.
Stage 4: Scheduling
If contact is established, the coordinator matches the patient's scheduling preferences, location, and insurance coverage with specialist availability. Prolonged specialist wait times represent a major barrier; if a specialist has a backlog extending beyond several weeks, the patient is statistically far more likely to cancel or fail to attend the appointment.
Stage 5: Pre-Visit Preparation and Loop Closure
Prior to the consultation, the patient must complete intake forms, transmit external records, and adhere to specialized instructions. Following the completed specialist visit, the receiving clinician must document their findings and transmit a detailed consult report back to the referring primary care provider. The loop is officially closed only when the referring clinician receives, reviews, and documents the specialist's findings, integrating the treatment plan into the patient's permanent care record.
The Expiration and Timeline of a Referral
A frequent source of operational friction and patient confusion is the lifespan and timeline of a referral. Clinical and operational leaders must establish clear guidelines regarding how long a referral remains valid. Administrative parameters vary, but an insurance authorization associated with a referral typically has a strict expiration date, commonly ranging from 30 to 90 days depending on the payer.
If a patient delays scheduling their appointment, the referral can expire, forcing the patient to return to their primary care provider for a new clinical evaluation and forcing the administrative team to re-initiate the prior authorization process from scratch. Furthermore, the clinical relevance of a referral letter decays over time. A specialist evaluating a patient six months after the initial referral was written may find that the patient's symptoms have changed, rendering the original clinical question and diagnostic history obsolete.
For health systems, these administrative delays and expired referrals represent a major source of patient attrition. When specialist backlogs extend for weeks, patients often abandon the care process entirely or seek an out-of-network provider who can offer faster access. This emphasizes the need for rapid outreach and real-time scheduling. A referral should not sit in an unmonitored queue, instead it should be acted upon within hours of creation to ensure the patient is booked before the referral expires or the patient disengages.
How to Get a Referral: Administrative and Insurance Hurdles
For patients navigating the healthcare system, securing a referral is often the primary barrier to accessing specialized care. From an operational perspective, the process begins when the patient schedules an evaluation with their primary care physician to assess their clinical symptoms. If the primary care physician determines that the patient's condition requires advanced diagnostics or specialized treatment, they will formally order the referral.
However, the necessity of a referral is heavily dictated by the patient's insurance plan design:
- Health Maintenance Organizations (HMOs): Under a strict HMO managed care framework, the primary care provider acts as a designated gatekeeper who must authorize all specialty transitions. The HMO will refuse to cover any specialist consultations, diagnostic imaging, or outpatient procedures unless a formal, approved referral is documented, protecting the payer from unnecessary utilization but adding significant administrative burden.
- Preferred Provider Organizations (PPO plans): PPO plans generally allow patients to seek specialty care directly without a formal PCP referral, though patients still face higher out-of-pocket costs and potential out-of-network penalties if they migrate outside the payer's preferred network.
Several exceptions exist under federal guidelines to protect patient safety and access. For example, under the No Surprises Act and federal emergency regulations, emergency department services and stabilization must be covered without prior administrative approval or referral mandates, regardless of whether the hospital is in-network. Similarly, federal protections ensure that female patients can access routine obstetrical and gynecological care from an in-network specialist without requiring a primary care referral.
In scenarios where a patient requires highly specialized care that is unavailable in-network, the administrative team must negotiate a Single Case Agreement (SCA) with the payer. An SCA is a customized, one-time contract that allows an out-of-network specialist to treat the patient while billing the payer at in-network rates, preserving care continuity and protecting the patient from unexpected balance billing.
The Financial and Operational Toll of Referral Leakage
For health system leadership, unmanaged referral outmigration represents a catastrophic loss of revenue and care continuity. To combat this drain effectively, organizations must utilize a precise taxonomy to distinguish between referral leakage, patient leakage, and network leakage:
| Taxonomy Element | Departmental Lens | Technical Operational Definition | Core Clinical & Financial Impact |
|---|---|---|---|
| Referral Leakage | Practice Operations | The percentage of formally ordered referrals that migrate to out-of-network or non-preferred providers when an in-network option was clinically viable. | Directly reduces downstream procedural and diagnostic volumes, compromising specialty clinic productivity. |
| Patient Leakage | Business Development | The physical exit of an attributed patient from the health system's care continuum to receive services at a competing health system. | Erodes long-term patient loyalty, with each lost patient representing an estimated lifetime value exceeding $600,000. |
| Network Leakage | Managed Care & Payers | The utilization of healthcare services by insured members outside of their contracted, preferred provider network. | Drives up the total cost of care for payers, violating customized discount agreements and triggering network penalties. |
The quantitative dimensions of this outmigration are staggering:
- Average Out-of-Network Referral Rate: Historically, health systems lose 55 to 65 percent of their outward referrals to out-of-network providers, meaning over half of their generated care volume is directed straight to competitors.
- Employed PCP Leakage: Even among physicians directly employed by a health system, nearly 45 percent of outbound referrals migrate out-of-network due to provider habit, lack of directory transparency, or scheduling delays.
- Annual System Loss: For a mid-sized health system, referral leakage translates to a massive revenue loss of $200 million to $500 million annually, with the average hospital losing 10 to 30 percent of its potential revenue.
- Annual Loss Per Referring PCP: Every primary care physician who refers patients out-of-network represents an estimated annual loss of $821,000 to $971,000 to the health system.
When a patient leaks out-of-network for an initial specialist consultation, the financial impact is rarely limited to that single visit. This outmigration initiates a procedural revenue cascade, where a single leaked orthopedic or cardiovascular consultation takes a massive volume of high-margin downstream services with it. The health system loses the technical fees for advanced diagnostic imaging, outpatient anesthesia, pathology, and post-acute physical therapy, severely depressing service-line margins and leaving expensive infrastructure underutilized.
Navigating Stark Law and Compliance
When confronted with the severe financial impact of referral leakage, health system executives often consider mandating that all employed physicians refer exclusively in-network. However, leadership teams are frequently hesitant to implement directed referral policies due to compliance concerns surrounding the federal Physician Self-Referral Law, commonly known as the Stark Law.
The Stark Law is a strict liability civil statute that prohibits physicians from referring Medicare or Medicaid patients for Designated Health Services (DHS) to an entity with which the physician or an immediate family member has a financial relationship, unless a specific exception applies. Because Stark Law is a strict liability statute, intent is completely irrelevant; even inadvertent administrative errors can result in devastating penalties, including the denial of all Medicare payments, mandatory refunds of collected reimbursements, and treble damages under the False Claims Act.
Fortunately, modernized Stark Law guidelines (including regulatory updates effective January 19, 2021) provide clear pathways for health systems to implement compliant directed referral requirements in physician employment and compensation agreements. According to legal analysis from Mintz, healthcare compliance officers must design directed referral programs around these three core standards:
- Percentage-Based and Ratio-Based Targets: Health systems are legally permitted to tie physician compensation bonuses or contract renewal conditions to a specific percentage or ratio of in-network referrals (for example, requiring that 90 percent of outpatient referrals remain in-network). Systems can offer structured financial bonuses for compliance, such as paying a 5 percent bonus for physicians who refer 80 percent in-network. However, the contract cannot make compensation contingent on the absolute number or value of referrals, as this would violate Stark's volume-and-value prohibitions.
- Mandatory Physician Carve-Outs: The directed referral policy must explicitly state in writing that the in-network requirement is completely overridden if the patient expresses an explicit preference for an out-of-network provider, if the patient's insurance plan or managed care contract dictates the use of a specific out-of-network provider, or if the physician determines in their independent clinical judgment that an in-network referral is not in the patient's best medical interest.
- Written and Signed Agreements: Any directed referral requirement must be clearly documented in a signed, written agreement (such as an employment contract or on-boarding agreement) to ensure transparency and regulatory audit readiness.
The Solution: AI-Driven Referral Automation with Steer Health
To stop the silent drain of referral leakage, health systems must transition from passive referral tracking (which merely monitors the status of a referral and alerts staff when it stalls) to active referral management, which automates the entire clinical and administrative workflow. Manual processes rely on paper faxes, physical work queues, and exhaustive phone tag, leading to a 45 percent administrative failure rate where faxed referrals never result in an attended appointment.
The key to recapturing this lost volume is removing operational friction, and this is where Steer Health transforms health system operations. Steer Health provides an AI-native referral management platform designed to capture, book, and close the loop on every clinical transition automatically. Built to connect seamlessly with 14+ electronic health record systems (including Epic, Cerner, and athenahealth) via FHIR R4 and HL7 standards, Steer's orchestration engine, Steer Studio, runs adjacent to the EHR, acting as a system of action that turns care demand into completed in-network visits without requiring a rip-and-replace of your existing EHR investment.
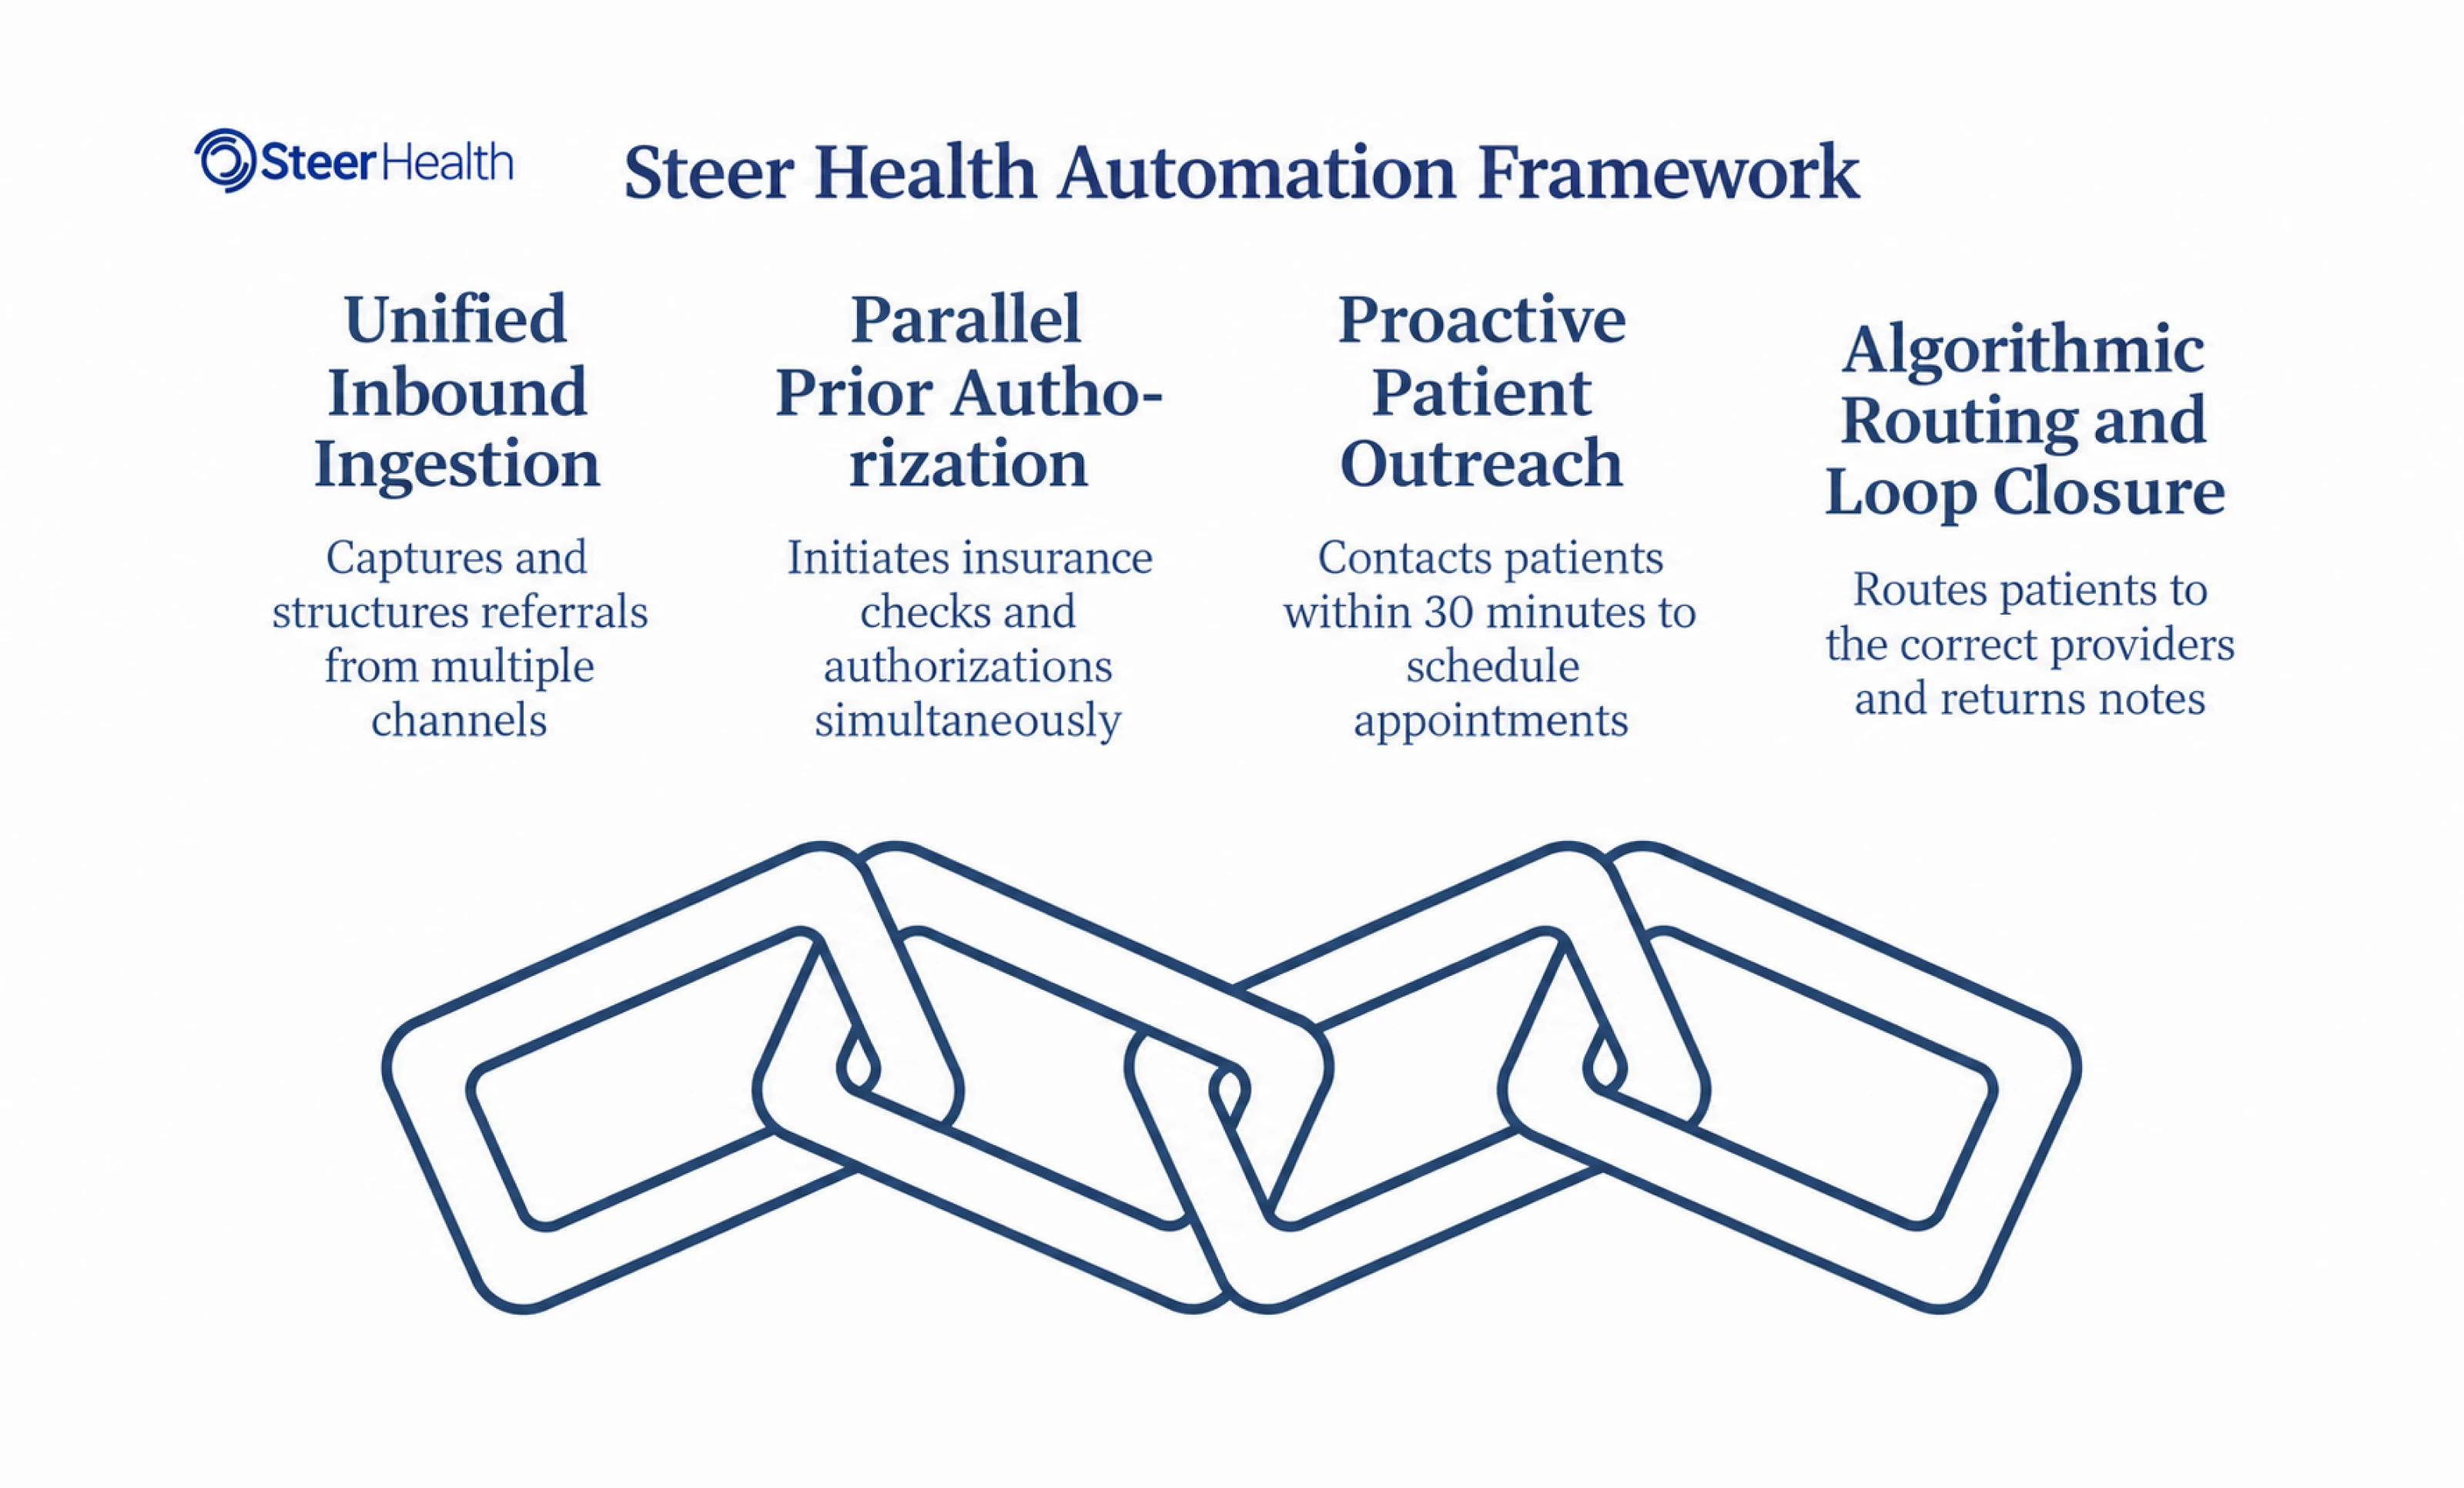
The Steer Health automation framework operates across four distinct phases:
1. Unified Inbound Ingestion — Steer's omnichannel digital front door, FastTrackCare, automatically captures and structures inbound referrals from every channel, including faxes, portals, emails, and direct EHR messages. Unstructured data is extracted via AI and logged instantly into a centralized intake queue, starting the clock the moment the referral arrives.
2. Parallel Prior Authorization — To eliminate administrative delays, Steer's financial gatekeeper agent, Apex, initiates insurance eligibility checks and prior authorization workflows the moment the referral is logged. Running financial clearance in parallel with booking prevents authorization delays from stalling the patient's care pathway.
3. Proactive Patient Outreach — Rather than expecting the patient to call the specialist, Luna, Steer's embedded AI voice agent, proactively contacts the referred patient within 30 minutes of referral receipt. Luna speaks in natural, conversational language to introduce the practice, verify demographic details, and schedule the appointment directly into the EHR, dramatically reducing patient disengagement.
4. Algorithmic Routing and Loop Closure — Steer Studio applies the health system's clinical and insurance rules to route the patient to the correct provider and sub-specialty, ensuring complex cases land in the appropriate slot. Once the consult occurs, Steer's care coordinator agent, Honi, ensures the specialist's consult note is returned to the referring primary care provider within 24 hours, completing the closed-loop requirement and protecting value-based contract metrics.
By replacing fragmented, manual handoffs with an automated system of action, health systems can recover millions in lost downstream margin. Every $1.00 (one dollar) invested in structured referral coordination, optimizing patient retention, and reducing outmigration, a health system receives an average of $31.36 back in return (an ROI of over 3,000%).
To help healthcare leaders identify where their referrals are slipping away, Steer Health offers a complimentary, 20-minute Lost Demand Assessment, providing a dollarized, source-by-source breakdown of your system's recovery potential. To schedule your assessment and protect your organization's operating margins, visit Steer Health Contact.